Today, I review, link to, and excerpt from The 2026 AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN Guideline for the Evaluation and Management of Acute Pulmonary Embolism in Adults: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines [PubMed Abstract] [Full-Text HTML] [Full-Text PDF]. Circulation. 2026 Mar 24;153(12):e977-e1051. doi: 10.1161/CIR.0000000000001415. Epub 2026 Feb 19.
All that follows is from the above resource.
Abstract
AIM
The “2026 AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN Guideline for the Evaluation and Management of Acute Pulmonary Embolism in Adults” is a de novo guideline that provides comprehensive recommendations for the evaluation, management, and follow-up of adult patients (≥18 years of age) with acute pulmonary embolism (PE). A key feature of this guideline is the introduction of the AHA/ACC Acute Pulmonary Embolism Clinical Categories, which enhance the precision of severity classification, prognosis assessment, and evidence-based therapeutic decision-making.METHODS
A comprehensive literature search was conducted from February 2024 to October 2024 to identify clinical studies, reviews, and other evidence conducted on human subjects that were published in English from MEDLINE (through PubMed), EMBASE, the Cochrane Library, Agency for Healthcare Research and Quality, and other selected databases relevant to this guideline. Select key studies published until April 2025 were added by the guideline writing committee as appropriate.STRUCTURE
The focus of this clinical practice guideline is an evidence-based and patient-centered approach for acute PE evaluation and management of the adult patient. This guideline encompasses the period from the onset of symptoms through clinical follow-up, focusing on risk outcomes assessment, clinical diagnosis of acute PE, appropriate use of adjunctive cardiovascular testing, and management in both the acute and early post-acute phases of PE. It addresses evidence-based diagnostic and management strategies (including pharmacological therapies, advanced interventional therapies, and in-hospital support) for acute PE and associated outcomes.Table of Contents
1.3.3.1.3.1.1.3.1.2.3.2.4.4.1.4.2.4.4.5.Top Take-Home Messages
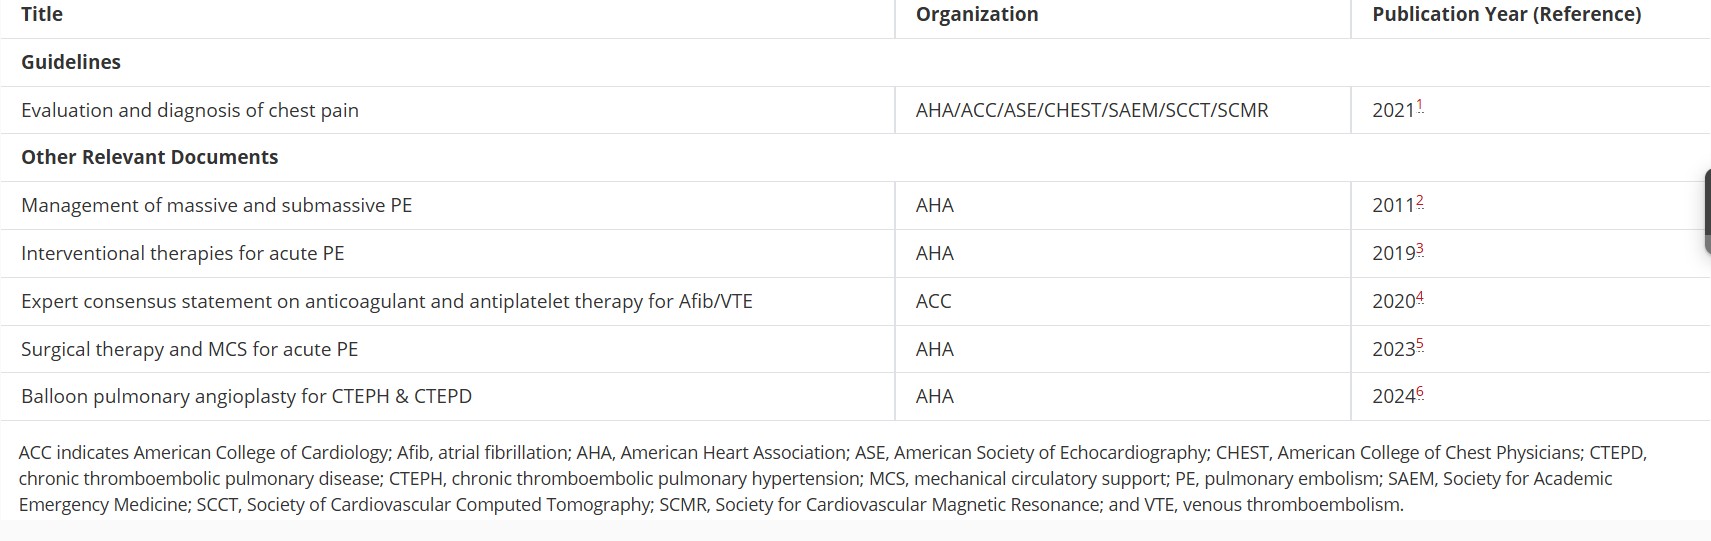
1.A new clinical classification scheme is presented, entitled “Acute Pulmonary Embolism Clinical Categories,” with 5 categories (A-E) and subcategories, ranging from low to high risk for adverse outcomes, in order to enhance the precision of severity classification, prognosis assessment, and evidence-based therapeutic decision-making for patients presenting with acute pulmonary embolism (PE).2.Patients with acute PE who are asymptomatic (AHA/ACC PE Category A) can safely be discharged home from the emergency room and do not need to be hospitalized.3.Early hospital discharge is generally recommended for patients with acute PE who are symptomatic but have a low clinical severity score (AHA/ACC PE Category B).4.Symptomatic patients with acute PE and an elevated clinical severity score, including those with elevated biomarkers and/or right ventricular dysfunction (AHA/ACC PE Category C), incipient cardiopulmonary failure (AHA/ACC PE Category D), and those with cardiopulmonary failure characterized by persistent hypotension (AHA/ACC PE Category E) should be hospitalized to optimize treatment strategies.5.Advanced therapies, including systemic thrombolysis, catheter-based thrombolysis, mechanical thrombectomy, and surgical embolectomy are reasonable for patients with acute PE in AHA/ACC PE Category E1 and can be considered for patients with acute PE in AHA/ACC PE Category D1-2.6.PE response teams (PERTs) are recommended to improve timeliness of care.7.In patients with acute PE who require initial parenteral anticoagulant therapy, low-molecular-weight heparin (LMWH) is recommended over unfractionated heparin (UFH).8.In patients with acute PE who are eligible for oral anticoagulation, direct oral anticoagulants (DOACs) are recommended over vitamin K antagonists (VKAs), unless contraindicated, to prevent recurrent venous thromboembolism (VTE) and reduce major bleeding.9.In patients with a first acute PE without a major reversible risk factor and in those with a persistent risk factor, continuing anticoagulation beyond the initial treatment phase (3-6 months) into the extended phase is recommended.10.Patients who have had acute PE should be asked about PE-related symptoms and functional limitations at every visit for at least 1 year to screen for chronic thromboembolic pulmonary disease (CTEPD) or other causes of dyspnea and functional limitation.Table 1. AHA and ACC Associated PublicationsACC indicates American College of Cardiology; Afib, atrial fibrillation; AHA, American Heart Association; ASE, American Society of Echocardiography; CHEST, American College of Chest Physicians; CTEPD, chronic thromboembolic pulmonary disease; CTEPH, chronic thromboembolic pulmonary hypertension; MCS, mechanical circulatory support; PE, pulmonary embolism; SAEM, Society for Academic Emergency Medicine; SCCT, Society of Cardiovascular Computed Tomography; SCMR, Society for Cardiovascular Magnetic Resonance; and VTE, venous thromboembolism.Table 2. Applying the American College of Cardiology/American Heart Association Class of Recommendation and Level of Evidence to Clinical Strategies, Interventions, Treatments, or Diagnostic Testing in Patient Care* (Updated December 2024)2.1. Definitions
Guideline-directed medical therapy: the term guideline-directed medical therapy encompasses clinical evaluation, diagnostic testing, and both pharmacological and procedural treatments. For these and all recommended drug treatment regimens, the reader should confirm dosage with product insert material and evaluate for contraindications and interactions. Recommendations are limited to drugs, devices, and treatments approved for clinical use in the United States.The ACC/AHA Acute PE Clinical Categories comprise a system designed to categorize the severity and prognosis of PE through the integration of various clinical, laboratory, and imaging parameters.Initial Treatment Phase describes the first 3 to 6 months of anticoagulation therapy after an acute PE. Extended Treatment Phase designates more than 6 months of anticoagulation therapy after an acute PE.2.2. Abbreviations
Abbreviation Meaning/Phrase APS antiphospholipid syndrome AUB abnormal uterine bleeding BMI body mass index BNP brain natriuretic protein BPA balloon pulmonary angioplasty CDL catheter-directed thrombolysis CKD chronic kidney disease CPET cardiopulmonary exercise testing CPR cardiopulmonary resuscitation CT computed tomography CTEPD chronic thromboembolic pulmonary disease CTEPH chronic thromboembolic pulmonary hypertension CTPA computed tomography pulmonary angiography CTV computed tomography venography DOAC direct oral anticoagulant DVT deep vein thrombosis ECMO extracorporeal membrane oxygenation ED emergency department eGFR estimated glomerular filtration rate FDA US Food and Drug Administration HFNC high-flow nasal cannula ICH intracranial hemorrhage ICU intensive care unit IVC inferior vena cava LMWH low molecular weight heparin LV left ventricle MAP mean arterial pressure MRA magnetic resonance angiography MT mechanical thrombectomy NE norepinephrine NEWS national early warning score NIV noninvasive mechanical ventilation PA pulmonary artery PE pulmonary embolism PESI pulmonary embolism severity index PH pulmonary hypertension PTE pulmonary thromboendarterectomy PVFR pulmonary venous flow reduction PVR pulmonary vascular resistance RCT randomized controlled trial RPVO residual pulmonary vascular obstruction RV right ventricle SPECT single-photon emission computed tomography SVR systemic vascular resistance TAPSE tricuspid annular plane systolic excursion TTE transthoracic echocardiogram UFH unfractionated heparin VD/VT alveolar dead space VE/VCO2 ventilatory efficiency VKA vitamin K antagonist V/Q ventilation/perfusion VTE venous thromboembolism